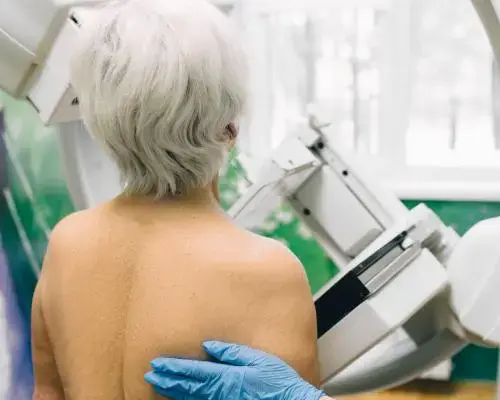
Systemic Underrepresentation in Clinical Trials
A global review of medical research reveals that women are significantly less likely than men to receive active treatment for identical health conditions, a disparity that medical professionals say directly endangers lives. The findings, highlighted in a recent analysis, underscore long-standing inequities in healthcare delivery that disproportionately affect women worldwide.
Breaking news
 Former German Intelligence Chief Faces Espionage Charges
 American Educator Analyzes French Student Demonstrations
 Massive Protests Erupt Across France Over Educational Funding Shortfalls
 French students and teachers protest inadequate school resources
The investigation, which examined treatment protocols across multiple countries, found that when men and women present with the same symptoms or diagnoses, healthcare providers are more inclined to prescribe experimental or aggressive therapies to men. Women, in contrast, are often directed toward placebos, conservative treatments, or delayed interventions. The lead author, a pharmacovigilance specialist at a clinical trials technology firm, noted that this pattern reflects systemic biases embedded in medical practice and research.
Historically, medical studies have prioritized male participants, skewing treatment guidelines and drug dosages toward male physiology. This oversight has left critical gaps in understanding how conditions manifest and respond to treatment in women. For instance, cardiovascular disease symptoms in women frequently differ from those in men, yet diagnostic criteria and therapeutic recommendations remain male-centric. The lack of female representation in trials means that clinicians often default to unproven or less effective treatments for women, exacerbating health disparities.
What Are the Long-Term Consequences of This Disparity?
Critics argue that this bias contributes to higher mortality rates among women with conditions like heart disease, cancer, and autoimmune disorders. Data from the World Health Organization estimates that gender-based gaps in treatment account for thousands of preventable deaths annually. Moreover, delayed or inadequate care can lead to disease progression, increased complications, and reduced quality of life. Advocates stress that addressing these inequities requires urgent reforms in clinical research, medical education, and healthcare policy.
The consequences extend beyond individual harm. Healthcare systems bear the cost of repeated hospitalizations and prolonged treatments resulting from misdiagnoses or suboptimal care. Meanwhile, women’s voices in medical decision-making remain marginalized, perpetuating cycles of mistrust in healthcare institutions.
Why does this bias persist despite awareness? Many attribute it to entrenched cultural norms and historical exclusion of women from medical research. Changing these deep-rooted practices requires institutional commitment and regulatory enforcement.
Frequently Asked Questions
How widespread is the issue? Studies across the U. S., Europe, and Asia consistently show similar patterns, suggesting the problem is global rather than isolated to specific regions.
What steps can address this disparity? Experts recommend mandating sex-disaggregated data in clinical trials, training providers on gender-specific care, and amplifying women’s participation in medical research governance.
The path forward demands accountability at every level of healthcare, from bench to bedside. Without it, the cost in lives will continue to mount.
